
 Dr. Tanmay Motiwala
Pediatric Surgeon, Raipur · Updated 30 Sep 2026 · 8 min read
A healthy baby who was laughing and playing suddenly pulls up their legs and screams. The crying stops for a few minutes. Then it starts again, just as sudden and just as strong. In between these bouts, your baby looks pale and tired out. Later, you see something scary in the nappy: red and brown slime like jelly, with almost no normal stool. This could be intussusception.
Sudden bouts of cramping tummy pain, with blood and slime (mucus) in the stool, are the classic warning signs of intussusception. It is one of the most serious bowel emergencies in young children. So it needs treatment within hours.
The good news: if we catch it in time, we can very often treat it without surgery.
What Is Intussusception?
The word sounds hard, but the idea is simple.
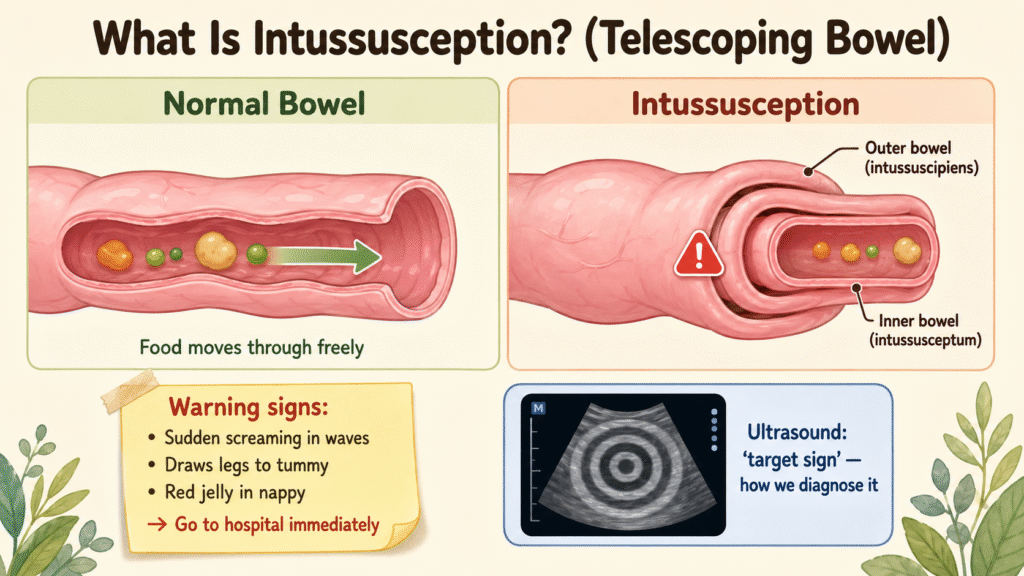
The bowel is a long, hollow tube. In intussusception, one part of this tube telescopes into the part next to it, like a sock you push inside out. The inner part then sticks inside the outer one.
When this happens:
- Nothing can pass through the blocked bowel
- The squeeze cuts down blood flow to the trapped inner part
- The bowel starts to swell. If nobody frees it, it starts to die
That is why it needs urgent treatment.
Who Gets Intussusception?
Intussusception is mainly a problem of young children. It is most common between 3 months and 3 years. The largest number of cases is in babies between 6 and 9 months of age. This is when weaning (starting solid food) begins. It is also when the small glands (lymph nodes) in the bowel wall are most active.
About 75% of all cases occur in the first 2 years of life, and 90% occur before age 3. Boys get it a little more often than girls.
In babies and toddlers under 2 years, it almost always starts on its own. Doctors cannot find a cause. But in older children (over 5 years), something inside the bowel more often starts it. Doctors call this a “lead point”. It may be a small pouch in the bowel (Meckel’s diverticulum), a growth on the bowel lining (polyp), or rarely a lymph gland cancer (lymphoma). Up to 60% of cases in older children have a cause we can find.
Warning Signs of Intussusception
The three classic signs are:
1. Sudden, severe, cramping tummy pain that comes and goes. The baby screams and pulls up the knees. Then the baby goes quiet and floppy for a few minutes, and then screams again. The pain comes in waves because the bowel keeps squeezing against the blockage, on and off. Parents often say the child looks well between bouts, and that is exactly right.
2. Vomiting. At first, the vomit is clear or milky (non-bilious). If the blockage gets worse, the vomit may turn yellow or green. This is a sign that the blockage is complete.
3. “Red currant jelly” stool. The hurt, swollen bowel lining sheds blood and slime (mucus). They come out together as dark red jelly in the nappy. This is a late sign. It means damage to the bowel has already started. Do not wait to see this before going to hospital.
A skilled doctor may also feel a sausage-shaped lump in the upper tummy. Also, the lower right part of the tummy often feels oddly empty, because the bowel that is usually there has telescoped away.
All three signs are present together in only about 25 to 30% of children. Do not wait for the full picture. If a young child has sudden bouts of crying that you cannot settle, with vomiting, go to a hospital. Go even if there is no blood in the stool.
How Is It Diagnosed?
A scan of the tummy that uses sound waves (ultrasound of the abdomen) is the best and safest way to confirm intussusception. It is fast, uses no radiation, and is close to 100% accurate.
What the scan doctor (radiologist) sees on ultrasound:
- A “target” or “doughnut” sign — rings of bowel inside bowel, one inside the other, seen from the front
- A “pseudokidney” sign — an oval, layered lump seen from the side
The scan usually confirms it within minutes. A simple case does not need an X-ray or CT scan.
How Doctors Treat Intussusception
In most cases — no surgery.
The usual first treatment is an air or fluid enema. It suits children who come in within the first 12 to 24 hours. Your child must also not be very unwell, with no sign of a hole in the bowel (perforation). Here is how it works:
The doctor passes a small tube into the back passage. Then the doctor gently pumps in air (or a special fluid) under pressure, watching on X-ray. This pressure pushes the telescoped part back out, like turning the sock the right way again. So the blockage opens up.
This method works in 70 to 90% of cases. In skilled centres, success rates come close to 95%.
When it works, the fix is complete. The blockage clears, the child passes stool normally within hours, and usually goes home the same day.
When does my child need surgery?
Your child needs an operation when:
- The bowel already has a hole (perforation), with signs of infection of the tummy lining (peritonitis) or free air on scans
- The child is in shock, has a blood infection (sepsis), or is very unwell, so the enema would be unsafe
- We have tried the enema and it did not work
- An older child has a lead point (like a Meckel’s diverticulum) that caused the intussusception. The surgeon then needs to remove the lead point itself
During surgery, I gently ease the telescoped bowel back out by hand. If part of the bowel has already died, I remove that part and join the two healthy ends.
Will Intussusception Come Back?
After a successful enema, intussusception comes back in about 10% of children. Most repeat attacks happen in the first 24–48 hours. That is why we keep children in hospital to watch them. A second enema usually works. After two or three repeat attacks, the surgeon may advise a check to look for a lead point.
What Every Parent Must Know
Intussusception is an emergency where time matters. The longer the bowel stays telescoped:
- The more it swells and the more damage it suffers
- The less likely the enema is to work
- The more likely surgery becomes
Go to a hospital immediately if your child (under 3 years old):
- Has sudden, severe bouts of crying and pulls up their legs
- Vomits and looks pale between episodes of pain
- Passes blood or jelly-like material in the stool
- Was well an hour ago and now screams and will not settle
Do not wait overnight. Do not give pain medicine and watch. This is one of the conditions where every hour matters.
When to See a Pediatric Surgeon
Any child who may have intussusception needs a check at a children’s surgery centre. The centre should have ultrasound and be able to do an enema reduction. Suppose a local hospital has seen your child and the scan is unclear. Then ask for a referral to a centre with children’s surgery experts.
Dr. Tanmay Motiwala is a pediatric surgeon in Raipur, Chhattisgarh, trained at AIIMS Jodhpur. He manages children with intussusception and other bowel emergencies from across Chhattisgarh and central India. For urgent cases, go directly to the nearest hospital with paediatric surgical facilities.
Related reading:
- Baby Not Passing Stool Since Birth? It Could Be Hirschsprung Disease
- Appendicitis in Children: When Stomach Pain Needs Surgery
- Constipation in Children: Causes, Treatment & When to See a Pediatric Surgeon
📋 This article is part of Dr. Motiwala’s Pediatric General & Abdominal Surgery in Raipur services — see the full range of conditions treated, what to expect, and when to see a pediatric surgeon.
Related conditions parents also read
- Appendicitis in children
- Pyloric stenosis (forceful vomiting in babies)
- Testicular torsion (sudden testicle pain)
Worried about your child? Dr. Tanmay Motiwala consults in Raipur, Jagdalpur & Rajim. Book an appointment or call +91 83190 84711.
⚠️ Important Disclaimer: This article is for general information and educational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. Every child’s condition is different — facts, prognosis, and management can vary significantly from case to case. Please consult a qualified pediatric surgeon for advice specific to your child. In an emergency, go to the nearest hospital immediately.
Sources: Coran’s Pediatric Surgery (7th ed); Rob & Smith Operative Pediatric Surgery (7th ed); DK Gupta Pediatric Surgery Vol 1. Further reading for parents: Intussusception, Great Ormond Street Hospital.