
 Dr. Tanmay Motiwala
Pediatric Surgeon, Raipur · Updated 5 Oct 2026 · 12 min read
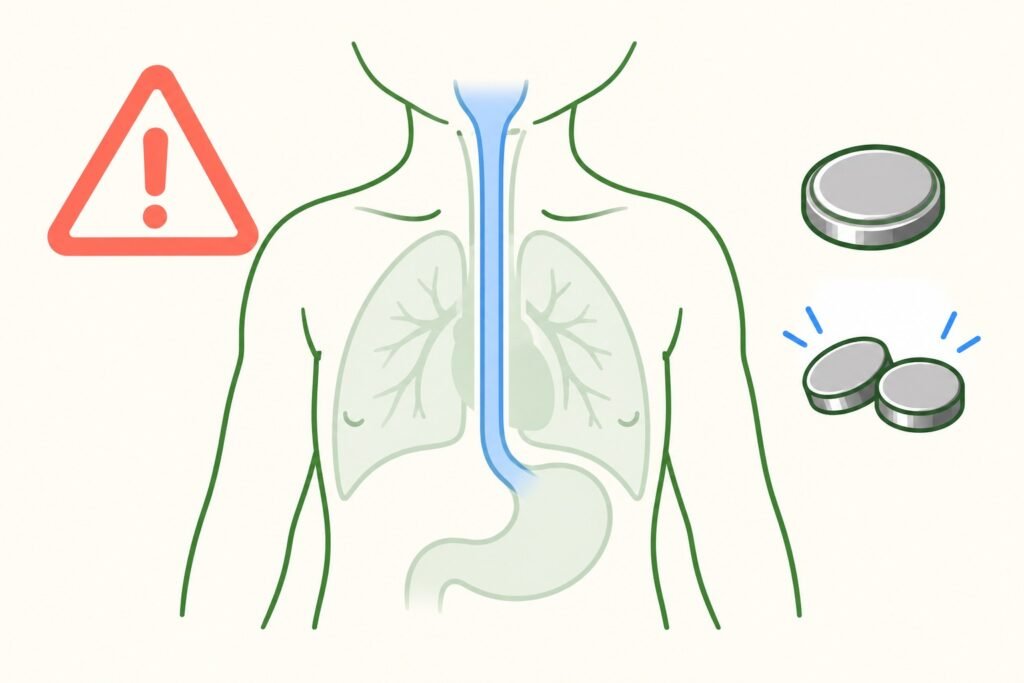
A toddler goes quiet in the next room. Then you notice that the remote control is open and its small, shiny coin battery is missing. Or a few tiny magnetic balls from a desk toy are gone. If you think your child swallowed a button battery or a magnet, do not wait to see what happens. Go to a hospital with a children’s surgery team straight away. This page explains why, and what to do on the way.
Most things a child swallows, like a coin, pass out in the stool without harm. These two are different. These are two objects where I never ask a parent to wait for signs before coming in. A doctor decides after an X-ray whether anything can be watched at home. For other objects, see our guide My child swallowed something: when is it an emergency?
Why a Button Battery Is So Dangerous
When a button battery gets stuck in the food pipe (the oesophagus), it touches the wet wall of the pipe. This completes a small electrical circuit. The current makes a strong alkali at the battery’s negative side. The alkali burns deep into the wall of the pipe. The battery also presses on the wall, and this adds to the damage. The burn can go on getting worse even after the doctor takes the battery out.
Injury starts fast. Damage to the lining can begin within 1 hour. Damage right through the muscle wall can happen within 2 to 4 hours. A used or “dead” battery still holds enough charge to cause this injury.
The batteries that carry the highest risk are the 3-volt lithium cells that are 20 mm wide or more (for example, the CR2032 type used in car keys, remotes and light-up toys). They are wide enough to jam in a small child’s food pipe. They are also strong enough to burn quickly. Batteries most often get stuck at the narrow places of the pipe: high in the neck, in the middle of the chest, and just above the stomach.
Button Battery Signs Can Be Missing or Look Like a Common Illness
Many children have no signs at all at first. Often no one sees the swallow happen. When signs do appear, they are easy to mistake for a cold, a chest infection or a stomach bug:
- Drooling, or refusing to feed or swallow
- Vomiting, or vomiting blood
- Cough, noisy breathing or a hoarse voice
- Chest pain, neck pain, irritability or fever
Because of this, a delay of hours, days or even weeks before the diagnosis is common, and delay is what leads to the worst injuries. If a young child has an unexplained cough, drooling or refusal to feed, and a battery could be missing from a toy or device at home, tell the doctor this at once.
What to Do Right Away After a Button Battery Swallow
- Go to the nearest hospital emergency department now. Do not wait for signs to appear. Do not wait for the battery to “pass”.
- Do not make your child vomit. Vomiting can push the battery back up toward the throat and airway, and can make the injury worse.
- Do not give food or drink on the way, except as described below. Your child may need a general anaesthetic for the removal, and a full stomach makes that riskier.
Honey on the way: The textbooks I use describe honey (or sucralfate, a coating medicine) as first aid when a battery swallow within the last 12 hours is known or strongly suspected, in children older than 1 year. The usual dose is 10 mL of honey every 10 minutes, up to 6 doses. Never give honey to a baby under 1 year, because of the risk of infant botulism. Honey does not replace removal of the battery, so do not stop to give it if that would delay getting to hospital.
How Doctors Find and Remove a Button Battery
The doctor takes X-rays from the front and from the side. A button battery shows a “double ring” on the front view and a “step” on the side view. A coin is a smooth, solid disc with no ring or step. Doctors can usually watch a coin that has reached the stomach, but a coin stuck in the food pipe also needs prompt removal.
A battery in the food pipe is a surgical emergency. The doctor should take it out with a camera through the mouth (an endoscopy) as soon as possible. The aim is within about 2 hours of the swallow, and immediately once the doctor finds it. Waiting beyond 2 to 4 hours raises the risk of a hole in the pipe, a link between the food pipe and the windpipe, and damage to nearby blood vessels.
What Happens If the Button Battery Is in the Stomach
If the X-ray shows the battery has already passed into the stomach, the plan depends on the size and the child. A small battery (under 20 mm) in a child over 1 year, with no signs and no known bowel problem, can often stay at home, with normal food and a check of the stool each day. The doctor repeats the X-ray in 10 to 14 days if it has not passed. The doctor takes the battery out of the stomach if the child has pain, vomiting, fever or vomits blood, if it is 20 mm or more in a child under 5 years and has not left the stomach after 24 to 48 hours, or if the child swallowed a magnet too. Your surgeon will decide, based on your child’s X-ray.
What Can Go Wrong After a Button Battery Injury, Honestly
When a battery is removed early, within about 2 hours and before the burn is deep, children usually heal fully and do well. When it stays longer, the risks are serious:
- A narrowing (stricture) of the food pipe. This can happen in about half or more of children whose burn goes deep all the way round the pipe. It shows up 2 to 4 weeks later, as trouble swallowing. Treatment means repeated stretching with a balloon or rod, often 12 to 18 sessions or more over months or years. If stretching fails, the surgeon may need to replace the food pipe with a piece of bowel or stomach.
- A link (fistula) between the food pipe and the windpipe. The child coughs or chokes on feeds and gets chest infections. It needs an operation to close it.
- A link to the main artery (the aorta) or another large vessel. This is the most dangerous complication. It causes sudden, massive bleeding, and most children who bleed this way do not survive. It can happen even after the doctor has taken the battery out.
- A weak or paralysed voice box (vocal cord), from injury to the nerve that runs beside the food pipe. The child may have a hoarse voice, a weak cry or noisy breathing.
- A hole in the pipe, infection in the chest (mediastinitis), and, rarely, infection of the spine bones. Some children need chest drains or an operation.
In national reports, about 1 to 3 in 100 children with a battery in the food pipe die, nearly all from a bleed from the artery or from severe infection in the chest. Children whose battery stayed for many hours can have lasting problems, such as trouble swallowing, feeding difficulty, repeated chest infections, and a weak voice. This is why speed matters more than anything else.
Why Magnets Are a Different Danger
One small magnet usually passes through the gut like a coin and comes out in the stool, as long as the child has no other gut problem. Two or more magnets, or one magnet plus a metal object, are a surgical emergency.
The magnets travel on their own through different loops of bowel. Then they pull toward each other across the walls of the bowel, and squeeze the tissue between them. That bit of bowel loses its blood supply, and the wall dies. This can cause a hole in the bowel (perforation) with infection of the tummy, a link between two loops of bowel (fistula), a twist of the bowel (volvulus), or a blockage. The “high-powered” magnets in desk toys, magnetic ball sets, building sets and fake piercing studs are many times stronger than ordinary magnets.
Signs can be quiet at first: a low fever, mild tummy cramps, nausea, or loss of appetite. Pressure damage takes hours to days, so a child can look well for a while. Later come severe tummy pain, green vomiting, a swollen tummy, a hard tender tummy, or blood in the stool. Many parents see magnetic balls as harmless toys, or never see the swallow, so the diagnosis is often late.
On an X-ray, several magnets can look clumped together in a line, ring or cluster, and they stay in the same place on repeat pictures. Seen from the front only, a stack of magnets can look like one object, so a side view is also needed.
Treatment for Swallowed Magnets
If the magnets are still in the food pipe or stomach, the doctor should take them out urgently with a camera, before they move on into the bowel. If they are beyond the stomach and the child has symptoms, or the X-rays show they are stuck in one place, the child needs an emergency operation (keyhole or open). The surgeon separates the magnets, checks every trapped bowel loop, and repairs small holes. Where the bowel wall has died, the surgeon removes that piece and joins the ends. A child with no signs, whose magnets are still moving along together, may stay in hospital for close watching, with repeat examinations and X-rays every 6 to 12 hours. If movement stops or the tummy becomes tender, surgery follows.
In published series, about 4 to 7 in 10 children who swallowed several high-powered magnets needed an operation to cut out or repair damaged bowel. When it is caught before widespread infection or bowel death, more than 95 in 100 survive, and most return to normal bowel function. Children who come late do worse: they can lose a long length of bowel, get abscesses in the tummy, or become seriously ill from infection.
Button Battery and Magnet Prevention: What Every Home Should Do
Children under 5 to 6 years are at highest risk, and the most severe battery injuries are in children under 3. Magnet injuries happen in toddlers, and also in older children who use magnetic balls as fake lip or tongue studs.
- Check every device that uses a coin battery: remote controls, car key fobs, kitchen scales, hearing aids, greeting cards and light-up toys. Close the battery cover with a screw or a child-proof lock. If it is not, keep the device away from children.
- Store spare and used batteries in a locked or high cupboard. Do not leave used batteries lying around. They can still burn.
- Keep high-powered magnet sets and magnetic balls out of homes with young children.
- Do not let teenagers use magnetic balls as piercings.
- If you ever suspect a swallow, go straight to hospital. Do not wait for signs.
What Every Parent Must Know
- A button battery in the food pipe can burn through its wall in 2 to 4 hours. Go to hospital at once, even if your child looks well.
- Do not make your child vomit. Do not wait for it to pass.
- Give honey on the way only to children over 1 year. Never delay going to hospital to give it.
- One magnet usually passes. Two or more magnets, or a magnet plus metal, need urgent care.
- Lock battery covers and keep strong magnets out of the house. Prevention is the best treatment.
When to See a Doctor
Go to an emergency department immediately if you know or suspect your child has swallowed a button battery, or more than one magnet, or a magnet and a metal object. Go the same way if your child has drooling, trouble swallowing, vomiting blood, a new cough or noisy breathing, or tummy pain with vomiting after any swallow you have seen.
Dr. Tanmay Motiwala is a pediatric surgeon in Raipur, Chhattisgarh, trained at AIIMS Jodhpur. He assesses and treats children who have swallowed dangerous objects, including batteries and magnets, from across Chhattisgarh and central India.
📋 This article is part of Dr. Motiwala’s General & Abdominal Surgery in Raipur services — see the full range of conditions treated, what to expect, and when to see a pediatric surgeon.
Related conditions parents also read
- My child swallowed something: when is it an emergency?
- My child keeps vomiting and passing nothing: is the bowel blocked?
- Is surgery safe for my child? 7 questions parents ask
Worried about your child? Dr. Tanmay Motiwala consults in Raipur, Jagdalpur & Rajim. Book an appointment or call +91 83190 84711.
⚠️ Important Disclaimer: This article is for general information and educational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. Every child’s condition is different — facts, prognosis, and management can vary significantly from case to case. Please consult a qualified pediatric surgeon for advice specific to your child.
Sources: Coran’s Pediatric Surgery (7th ed), Ch. 86 (Foreign Bodies and Ingestion); DK Gupta, Pediatric Surgery: Diagnosis and Management, Vol. 5, Ch. 31; Roy Choudhury, Pediatric Surgery, Ch. 29. Further reading: the National Capital Poison Center button battery ingestion guidance.