
 Dr. Tanmay Motiwala
Pediatric Surgeon, Raipur · Updated 30 Sep 2026 · 7 min read
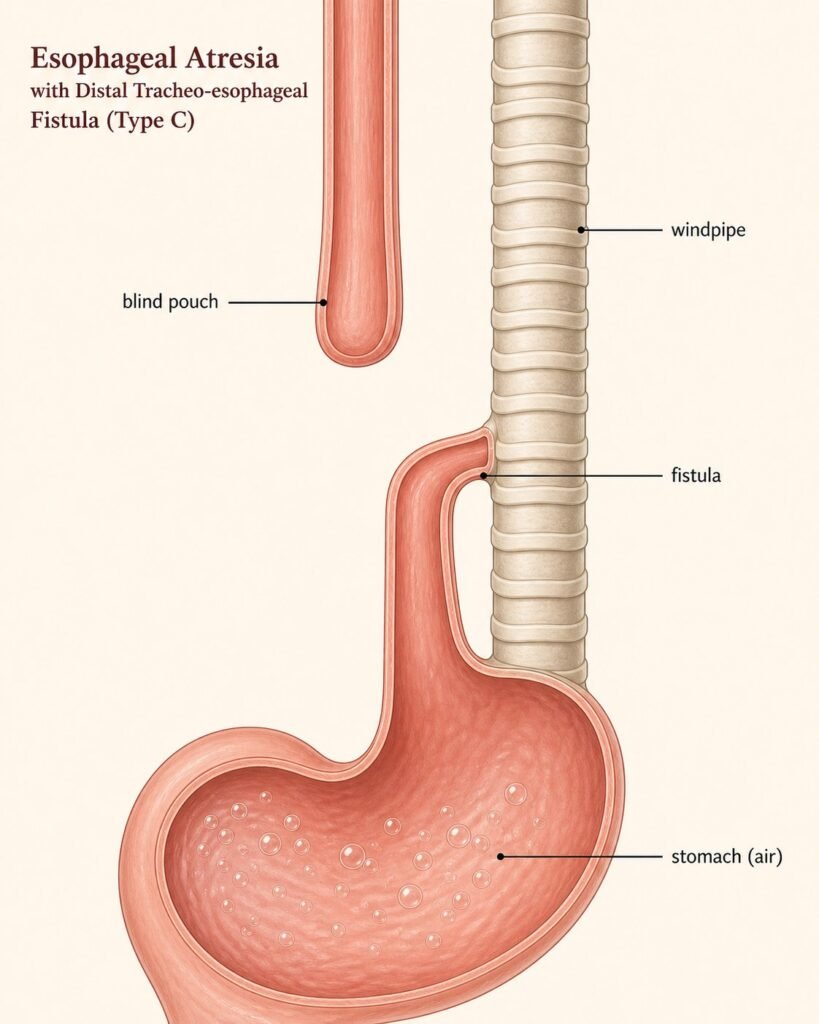
The delivery went well, but within hours something is not right. Your newborn keeps making frothy, bubbly saliva and drools far more than seems normal. At the first feed, the baby coughs, splutters and briefly turns blue. The nurses try to pass a feeding tube, but it will not go down. This is a frightening start for any parent. Yet it points to a condition pediatric surgeons know well and can repair: esophageal atresia.
Esophageal atresia means the food pipe (esophagus) did not form as one complete tube before birth. Very often there is also an abnormal link between the food pipe and the windpipe. Doctors call this a tracheo-esophageal fistula (TEF). In this article I explain what it means, why it happens, how we treat it, and, honestly, what the outlook is.
What Esophageal Atresia Actually Means
In the first weeks of pregnancy, a single tube should split neatly into two. The windpipe (for air) sits at the front, and the food pipe (for milk) sits behind it. In esophageal atresia this split is incomplete. The upper food pipe ends in a blind pouch that goes nowhere. So saliva and milk have no way down to the stomach, and that is why the baby froths, drools and chokes.
In most babies, about 85 in 100, the lower part of the food pipe also joins the windpipe (the fistula). In a smaller group, about 6 in 100, there is no link at all, and the two ends of the food pipe lie far apart. We call this the “long-gap” type, and it needs a different plan.
Signs of Esophageal Atresia and How We Confirm It
Sometimes there is a clue before birth. The pregnancy scan may show too much fluid around the baby (polyhydramnios), sometimes with a small or missing stomach bubble. After birth, the typical signs are:
- Frothy, bubbly saliva and constant drooling that nurses must suck out.
- Coughing, choking or turning blue with the first feeds.
- A feeding tube that will not pass down to the stomach. Instead, it curls back in the blind pouch.
Confirming it is quick and simple. The team passes a soft tube, and an X-ray shows it coiled in the upper pouch instead of reaching the stomach. This tells us the food pipe is blocked. Also, the pattern of gas in the tummy tells us which type it is.
Why We Check the Heart and Other Organs First
Esophageal atresia often does not come alone. Between half and two-thirds of babies (50 to 70%) have one or more other differences present from birth. Doctors screen for these with a checklist called VACTERL. It covers the spine, the anus, the heart, the kidneys and the limbs.
Heart defects are the most common of these, seen in roughly 1 in 4 babies. They are also the single biggest factor in how well a baby does. So the team does a heart scan (echocardiogram) before surgery. This scan is not just routine. It also shows whether the main artery (the aorta) curves to the right. That happens in a small number of babies, and it tells the surgeon which side of the chest to operate through.
Treating Esophageal Atresia: The Operation
Before surgery, nurses keep the baby head-up. A special double-channel tube (a Replogle tube) keeps the blind pouch empty of saliva, so saliva cannot spill into the lungs. The baby gets no feeds by mouth.
The repair is an operation, usually in the first few days of life. The surgeon closes the abnormal link to the windpipe. Then the surgeon joins the two ends of the food pipe so milk can pass to the stomach. Sometimes the two ends are too far apart (the long-gap type). Here we avoid forcing them together. Instead, the surgeon may wait some weeks for the gap to narrow, use a lengthening technique, or in some cases replace the food pipe. The right route depends on each baby.
Outlook After Esophageal Atresia Repair
First, the good news. For a baby of good birth weight with no major heart defect, survival after repair today is excellent. The outcome depends mainly on those two things: birth weight and the heart.
But it would be wrong to pretend the repair ends the story. Several issues are common afterwards, and parents should know them in advance. All of them are manageable:
- Acid reflux is very common (roughly 3 to 7 children in 10) and often needs medicine. A few children need a further anti-reflux operation.
- The join can narrow over time. Strict studies report this in up to 8 in 10 children, and it makes food stick. Many need at least one gentle stretch (dilatation), sometimes more than once.
- The windpipe can be soft (tracheomalacia). This gives a barky cough or noisy breathing, which usually improves as the child grows.
Because of these issues, a child born with esophageal atresia needs regular follow-up for the first years. Still, the great majority grow up eating, growing and thriving.
The “Later” Version: the H-Type to Know
In a small number of children the food pipe is complete, but a small link to the windpipe remains (an “H-type” fistula). Here the feeding tube does pass, so doctors do not pick it up at birth. It shows up later as coughing or choking during feeds and repeated chest infections. If your child has that pattern, mention it to the doctor.
What Every Parent Must Know
- A newborn who froths, drools and chokes with feeds, and whose feeding tube will not go down, may have esophageal atresia. A simple X-ray confirms it.
- Surgeons repair it in the first days of life. They join the food pipe and close the windpipe link.
- The team does a heart scan first, because heart defects are the commonest linked problem and matter most for outcome.
- For a well-grown baby without a serious heart defect, the outlook is excellent. But reflux and narrowing of the join are common and need follow-up.
When to See a Pediatric Surgeon
Doctors almost always find esophageal atresia in the hospital soon after birth, and the newborn team will call a pediatric surgeon straight away. Was your baby born elsewhere? If the baby is frothing, choking with feeds, or a tube would not pass, ask for an urgent surgical referral. An older child may have unexplained choking during feeds and repeated chest infections. In that case, a surgical opinion is worthwhile to look for the rarer H-type.
Dr. Tanmay Motiwala is a pediatric surgeon in Raipur, Chhattisgarh, trained at AIIMS Jodhpur. He manages newborn surgical conditions — including esophageal atresia — for babies referred from across Chhattisgarh and central India, and can guide parents through diagnosis, surgery and the follow-up that matters afterwards.
Related reading:
- My Baby Throws Up Forcefully After Every Feed — Could It Be Pyloric Stenosis?
- My Baby’s Vomit Turned Green — Why This Is an Emergency
- My Newborn Is Still Yellow After Two Weeks — When Is Jaundice Dangerous?
📋 This article is part of Dr. Motiwala’s Neonatal & Newborn Surgery in Raipur services — see the full range of conditions treated, what to expect, and when to see a pediatric surgeon.
Related conditions parents also read
- Pyloric stenosis (forceful vomiting after every feed)
- Green (bilious) vomiting in a baby — why it is an emergency
- Biliary atresia (a newborn still yellow after two weeks)
Worried about your child? Dr. Tanmay Motiwala consults in Raipur, Jagdalpur & Rajim. Book an appointment or call +91 83190 84711.
⚠️ Important Disclaimer: This article is for general information and educational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. Every child’s condition is different — facts, prognosis, and management can vary significantly from case to case. Please consult a qualified pediatric surgeon for advice specific to your child.
Sources: Coran’s Pediatric Surgery (7th ed), Ch. 69 (Congenital Anomalies of the Esophagus); Rob & Smith Operative Pediatric Surgery (7th ed). Further reading for parents: Oesophageal atresia with tracheo-oesophageal fistula, Great Ormond Street Hospital.